
Your Health, We Care


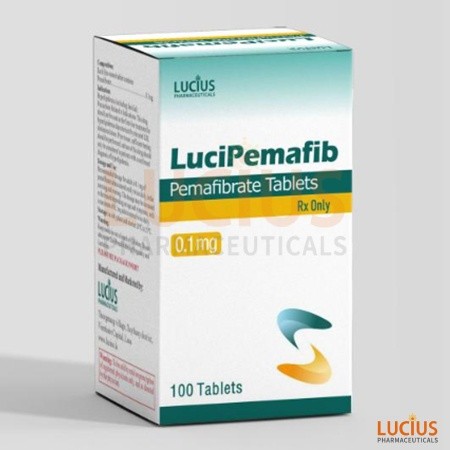
Another NameParmodia、派龙达、佩玛贝特
IndicationsIndicated for the treatment of hyperlipidemia associated with elevated triglycerides.
Specs


Telegram name: Vira
Name: LUCIUS
No.:0085253923643
Pemafibrate (LuciPemafib) is a selective peroxisome proliferator-activated receptor alpha (PPARα) modulator (SPPARMα) indicated for the treatment of hyperlipidemia (including familial hyperlipidemia).
Pemafibrate (LuciPemafib) is indicated for patients with hyperlipidemia whose lipid levels remain inadequately controlled after basic therapies such as dietary therapy, and it acts by lowering plasma triglyceride (TG) concentrations and increasing high-density lipoprotein cholesterol (HDL-cholesterol). Pemafibrate (LuciPemafib) is a prescription drug and must be used under a physician's prescription.

Sufficient examinations should be performed before considering Pemafibrate (LuciPemafib), and Pemafibrate (LuciPemafib) should be considered only for patients with an established diagnosis of hyperlipidemia.
Renal function should be checked before administration. Because Pemafibrate (LuciPemafib) may cause rhabdomyolysis accompanied by acute worsening of renal function, renal function should be checked at the time of administration and the starting dose and dosing interval should be determined accordingly.
Serum lipid levels should be checked periodically during administration to confirm the effect of Pemafibrate (LuciPemafib); if no effect of Pemafibrate (LuciPemafib) is observed, administration should not be continued indefinitely and should be discontinued.
Pemafibrate (LuciPemafib) may affect liver function and liver function test values, and liver function tests should be performed periodically during administration.
Low-density lipoprotein cholesterol (LDL-cholesterol) levels may increase during Pemafibrate (LuciPemafib) administration, and LDL-cholesterol levels should be checked periodically during administration.
For patients with abnormal renal function, concomitant use of HMG-CoA reductase inhibitors (statins) should be avoided unless judged unavoidable in treatment; when unavoidable, concomitant use should be started at a low dose, with periodic renal function tests, and monitoring for subjective symptoms (muscle pain, weakness), creatine kinase (CK) elevation, increased blood and urine myoglobin, and worsening renal function such as increased serum creatinine.
Dietary therapy, which is the basis of hyperlipidemia treatment, should be implemented in advance, and exercise therapy and reduction of risk factors for ischemic heart disease such as hypertension and smoking should be fully considered.
Oral administration, twice daily, in the morning and evening.
For adults, the dose of Pemafibrate (LuciPemafib) is 0.1 mg twice daily, administered orally in the morning and evening.
The dose may be appropriately increased or decreased according to age and symptoms, with a maximum dose of 0.2 mg twice daily (i.e., 0.4 mg daily).
Not established.
Do not administer to pregnant women or women who may be pregnant.
Breastfeeding should preferably be avoided.
The safety and efficacy in pediatric patients have not been established.
Geriatric patients generally have reduced physiological function; attention should be paid to the occurrence of adverse reactions, and administration should be cautious with sufficient observation.
Do not administer to patients with severe hepatic impairment, cirrhosis of Child-Pugh class B or C, or biliary obstruction; because Pemafibrate (LuciPemafib) may aggravate hepatic impairment and plasma concentrations of Pemafibrate (LuciPemafib) may increase.
For patients with hepatic impairment (e.g., cirrhosis of Child-Pugh class A) or a history of hepatic impairment, consideration should be given to reducing the Pemafibrate (LuciPemafib) dose when necessary, and the need to increase the Pemafibrate (LuciPemafib) dose should be carefully judged; abnormal changes in liver function test values may occur, and plasma concentrations of Pemafibrate (LuciPemafib) may increase in patients with hepatic impairment.
Patients with renal impairment and eGFR below 30 mL/min/1.73 m² may develop rhabdomyolysis. Renal function should be checked at administration, and dosing should be started at a low dose, reduced, or the dosing interval prolonged; the maximum dose is 0.2 mg daily.
In patients with renal impairment (mild, moderate, severe, or end-stage renal failure), increased exposure was observed after administration compared with the group with normal renal function, but no exposure increase dependent on the degree of renal impairment was observed. Patients with end-stage renal failure on hemodialysis are handled in the category of eGFR below 30 mL/min/1.73 m².
If rhabdomyolysis accompanied by acute worsening of renal function occurs, administration should be stopped immediately and appropriate measures taken. If abnormal changes in liver function tests occur, whether to reduce or discontinue should be judged based on the liver function test results; if signs of aggravated hepatic impairment appear, discontinue. If LDL-cholesterol levels continue to rise during administration, manage based on clinical judgment.
Pemafibrate (LuciPemafib) is primarily metabolized by CYP2C8, CYP2C9, and CYP3A, and is a substrate of OATP1B1 and OATP1B3.
When used concomitantly with the following drugs, consideration should be given to reducing the Pemafibrate (LuciPemafib) dose when necessary, and the need to increase the Pemafibrate (LuciPemafib) dose should be carefully judged: clopidogrel sulfate; clarithromycin, HIV protease inhibitors such as ritonavir; fluconazole.
When used concomitantly with anion exchange resins such as cholestyramine or colestipol, plasma concentrations of Pemafibrate (LuciPemafib) may decrease, and administration should be separated as much as possible when used concomitantly.
When used concomitantly with strong CYP3A inducers such as carbamazepine, phenobarbital, phenytoin, or foods containing St. John's wort, plasma concentrations of Pemafibrate (LuciPemafib) may decrease and the effect of Pemafibrate (LuciPemafib) may be diminished; concomitant use should be avoided or carefully judged.
Concomitant use with cyclosporine or rifampin is contraindicated and must not be used together.
Renal Impairment
Patients with eGFR of 60 mL/min/1.73 m² or higher (normal renal function): administer according to the usual dosage and administration, i.e., 0.1 mg twice daily, maximum 0.2 mg twice daily.
Patients with eGFR from 30 mL/min/1.73 m² to less than 60 mL/min/1.73 m² (mild to moderate renal impairment): exposure increase dependent on the degree of renal impairment was not confirmed; administer according to the usual dosage and administration, but perform periodic renal function tests and observe sufficiently during administration.
Patients with eGFR below 30 mL/min/1.73 m² (severe renal impairment): start at a low dose, reduce the dose, or prolong the dosing interval; the maximum dose is 0.2 mg daily.
Patients on hemodialysis (end-stage renal failure): handled in the category of eGFR below 30 mL/min/1.73 m² as above, with a maximum dose of 0.2 mg daily.
Because patients with eGFR below 30 mL/min/1.73 m² may develop rhabdomyolysis, renal function should be checked and the dose adjusted at administration.
Hepatic Impairment
Do not administer to patients with severe hepatic impairment, cirrhosis of Child-Pugh class B or C, or biliary obstruction; for patients with hepatic impairment (e.g., cirrhosis of Child-Pugh class A) or a history of hepatic impairment (other than those contraindicated above), consideration should be given to reducing the Pemafibrate (LuciPemafib) dose when necessary, and the need to increase the Pemafibrate (LuciPemafib) dose should be carefully judged.
Geriatric patients have generally reduced physiological function; attention should be paid to the occurrence of adverse reactions, and administration should be cautious with sufficient observation.
Do not administer to the following patients:
Patients with a history of hypersensitivity to Pemafibrate (LuciPemafib) components.
Patients with severe hepatic impairment, cirrhosis of Child-Pugh class B or C, or biliary obstruction.
Patients with gallstones. Gallstone formation has been reported with Pemafibrate (LuciPemafib).
Pregnant women or women who may be pregnant.
Patients currently using cyclosporine or rifampin.
Rhabdomyolysis
Rhabdomyolysis characterized by muscle pain, weakness, creatine kinase (CK) elevation, and increased blood and urine myoglobin may occur, and may be accompanied by severe renal impairment such as acute kidney injury. If this occurs, stop administration immediately and take appropriate measures. High-risk populations are patients with renal impairment and patients receiving concomitant HMG-CoA reductase inhibitors. Monitoring and management: monitor for muscle pain, weakness, creatine kinase elevation, increased blood and urine myoglobin, and increased serum creatinine; if abnormalities occur, stop immediately.
Hepatic Dysfunction, Jaundice
Hepatic dysfunction and jaundice may occur. Monitoring and management: perform periodic liver function tests during administration; if abnormal changes occur, reduce or discontinue; if signs of aggravated hepatic impairment appear, discontinue and take appropriate measures.
Hepatic: cholelithiasis; hepatic function abnormalities, aspartate aminotransferase (AST) elevation, alanine aminotransferase (ALT) elevation. Check liver function and abdominal symptoms periodically, and take appropriate measures if abnormalities occur.
Muscular: creatine kinase (CK) elevation, increased blood myoglobin, muscle pain. If muscle pain or weakness occurs, check creatine kinase and myoglobin, and discontinue if abnormal.
Skin: rash, pruritus. Take appropriate measures for rash or pruritus, and discontinue if necessary.
Other: diabetes (including worsening); increased glycated hemoglobin, increased LDL, increased blood uric acid. Monitor blood glucose, glycated hemoglobin, lipids, and uric acid, and take appropriate measures if abnormalities occur.
Pemafibrate (LuciPemafib) is a therapeutic agent for hyperlipidemia, and its efficacy is reflected in serum lipid levels; serum lipid levels should be checked periodically during administration. If no effect of Pemafibrate (LuciPemafib) is observed, administration should not be continued indefinitely and should be discontinued. Check serum lipid levels periodically during administration, and discontinue if no effect is observed.
Pemafibrate (LuciPemafib) may affect liver function and liver function test values, and hepatic dysfunction and jaundice have been reported (incidence unknown). Pemafibrate (LuciPemafib) is metabolized by the liver and may affect hepatocyte function, potentially causing hepatic dysfunction and jaundice.
Perform periodic liver function tests during administration; if abnormal changes in liver function test values occur, judge whether to reduce or discontinue based on the results; if signs of aggravated hepatic impairment appear, discontinue and take appropriate measures.
LDL-cholesterol levels may increase during Pemafibrate (LuciPemafib) administration. Check LDL-cholesterol levels periodically during administration and manage based on clinical judgment.
Pemafibrate (LuciPemafib) may cause rhabdomyolysis accompanied by severe renal impairment such as acute kidney injury, with acute worsening of renal function. Rhabdomyolysis is characterized by muscle pain, weakness, creatine kinase (CK) elevation, and increased blood and urine myoglobin. Monitor subjective symptoms such as muscle pain and weakness, creatine kinase elevation, increased blood and urine myoglobin, and increased serum creatinine; if these abnormalities occur, stop administration immediately and take appropriate measures.
Gallstone formation has been reported with Pemafibrate (LuciPemafib) and may aggravate cholelithiasis. Observe sufficiently when administering to patients with a history of gallstones; take appropriate measures if manifestations related to cholelithiasis occur, and discontinue if necessary.
Pemafibrate (LuciPemafib) is primarily metabolized by CYP2C8, CYP2C9, and CYP3A, and is a substrate of OATP1B1 and OATP1B3.
Cyclosporine: Concomitant use increases plasma concentrations of Pemafibrate (LuciPemafib); do not use concomitantly.
Rifampin: Concomitant use increases plasma concentrations of Pemafibrate (LuciPemafib); do not use concomitantly.
HMG-CoA reductase inhibitors (statins such as pravastatin sodium, simvastatin, fluvastatin sodium, etc.): Rhabdomyolysis accompanied by acute worsening of renal function is likely to occur. If subjective symptoms (muscle pain, weakness), creatine kinase (CK) elevation, increased blood and urine myoglobin, or worsening renal function such as increased serum creatinine occur, stop administration immediately.
Clopidogrel sulfate: Concomitant use increases plasma concentrations of Pemafibrate (LuciPemafib); when used concomitantly, consider reducing the Pemafibrate (LuciPemafib) dose when necessary, and carefully judge the need to increase the Pemafibrate (LuciPemafib) dose.
Clarithromycin, HIV protease inhibitors such as ritonavir: Concomitant use increases plasma concentrations of Pemafibrate (LuciPemafib); when used concomitantly, consider reducing the Pemafibrate (LuciPemafib) dose when necessary, and carefully judge the need to increase the Pemafibrate (LuciPemafib) dose.
Fluconazole: Increased plasma concentrations of Pemafibrate (LuciPemafib) have been reported with concomitant use; manage accordingly based on the increased plasma concentrations of Pemafibrate (LuciPemafib).
Anion exchange resins (cholestyramine, colestipol): Plasma concentrations of Pemafibrate (LuciPemafib) may decrease; separate administration as much as possible when used concomitantly.
Strong CYP3A inducers (carbamazepine, phenobarbital, phenytoin, foods containing St. John's wort, etc.): Plasma concentrations of Pemafibrate (LuciPemafib) may decrease and the effect of Pemafibrate (LuciPemafib) may be diminished. Avoid concomitant use or judge carefully.
Telegram name: Vira
Name: LUCIUS
No.:0085253923643
